Why the Order of Draw Matters on the CPT Exam
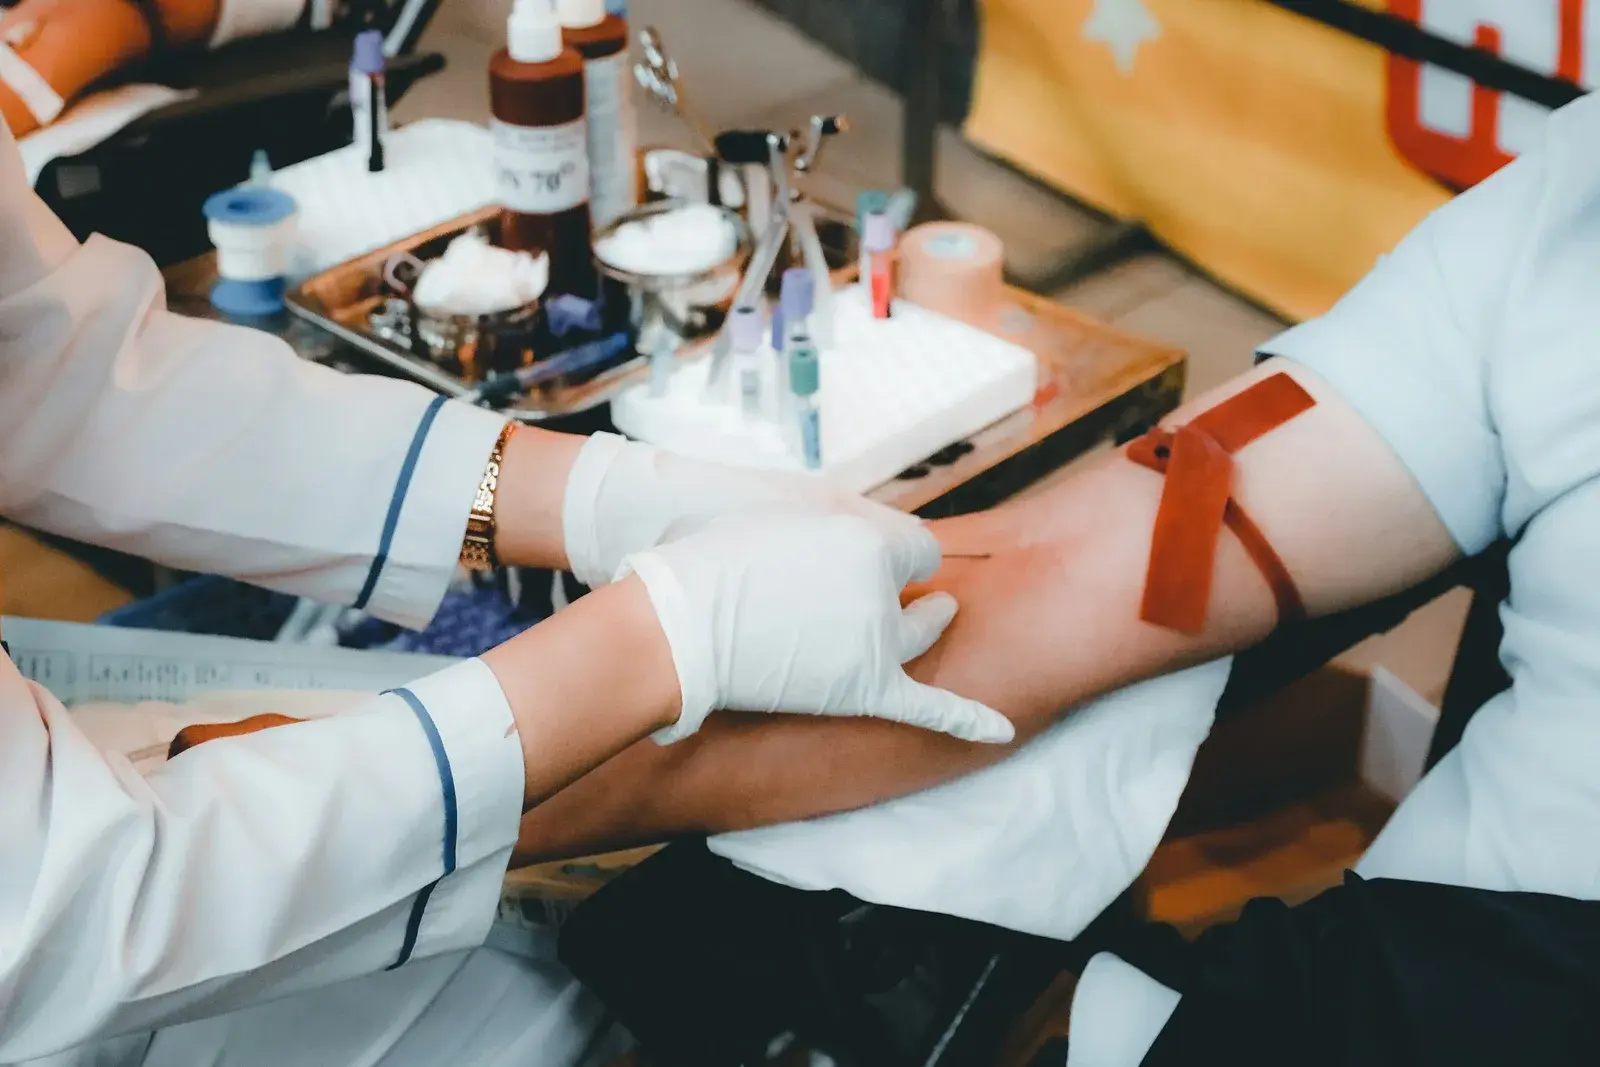
On every national phlebotomy certification examination — including the NHA CPT, ASCP PBT, and AMT RPT — questions on the order of draw appear repeatedly. The order of draw is not arbitrary: it was established by the Clinical and Laboratory Standards Institute (CLSI H3-A6 standard) to eliminate cross-contamination between tube additives.
If blood touches the needle inside a tube containing potassium EDTA (lavender top) and carries even a trace amount of EDTA into a subsequent tube used for electrolyte testing, the patient's reported potassium level will appear critically, lethally elevated (hyperkalemia). Knowing the exact order, tube additive, inversion count, and laboratory department for each color is mandatory to pass.
Drill these rules with our Phlebotomy cheat sheet or take a free timed CPT practice test.
Official CLSI Phlebotomy Order of Draw Chart
Always draw evacuated blood collection tubes in this exact sequence for multi-tube venipuncture:
| Order & Stopper Color | Common Additive | Mechanism of Action | Inversion Count | Common Lab Tests / Department |
|---|---|---|---|---|
| 1. Blood Cultures (Yellow SPS / Bottles) | SPS (Sodium Polyanethol Sulfonate) or aerobic/anaerobic culture broth | Inactivates complement and aminoglycosides; prevents blood clotting while allowing microorganisms to multiply. | 8–10 inversions | Microbiology department (FUO / bacteremia / septicemia workups). Drawn first to prevent microbial contamination. |
| 2. Light Blue | Sodium Citrate (9:1 blood-to-anticoagulant ratio) | Binds ionic calcium to block coagulation cascade reversibly. | 3–4 inversions (Very gentle) | Coagulation department (PT / INR, aPTT / PTT, D-Dimer, Fibrinogen). Must be filled to the indicator line (9:1 ratio). |
| 3. Red (Glass or Plastic) | Glass: None (silicone coated) Plastic: Clot activator (silica particles) | Promotes coagulation. Blood clots naturally in 30–60 minutes. Produces serum upon centrifugation. | Plastic: 5 inversions Glass: 0 inversions | Chemistry, Serology, Immunology, Blood Bank (ABO/Rh typing, Crossmatch, antibody screens). |
| 4. Gold / Tiger Top (SST) | Clot activator + Thixotropic Gel Separator | Silica accelerates clotting; polymer gel shifts during centrifugation to form a physical barrier between serum and clot. | 5 inversions | Chemistry department (BMP, CMP, Lipid panel, Thyroid TSH/T4, Cardiac troponin, Hepatic function). |
| 5. Light Green / Green (PST) | Lithium Heparin (or Sodium Heparin) + Gel Separator (PST) | Inhibits thrombin formation and factor Xa. Produces plasma (no clotting wait needed). | 8–10 inversions | STAT Chemistry, electrolytes, ammonia, arterial blood gases (ABGs on ice), troponin STAT runs. |
| 6. Lavender / Purple | K2 EDTA (dipotassium) or K3 EDTA (spray-coated) | Irreversibly binds (chelates) calcium; preserves cellular morphology of blood cells without distortion. | 8–10 inversions | Hematology department (Complete Blood Count / CBC, Hemoglobin & Hematocrit H&H, ESR, WBC differential, HbA1c). |
| 7. Gray | Sodium Fluoride (antiglycolytic agent) + Potassium Oxalate (anticoagulant) | Sodium fluoride inhibits enolase enzymes to preserve glucose for up to 72 hours; oxalate precipitates calcium. | 8–10 inversions | Chemistry department (Fasting blood glucose, Oral Glucose Tolerance Test / OGTT, blood alcohol / ethanol levels, lactic acid on ice). |
| 8. Royal Blue (Specialty) | Trace element K2 EDTA (purple stripe) or Clot Activator (red stripe) | Chemically pure plastic/rubber specifically certified trace-element-free (<5 ppb). | 8–10 inversions | Toxicology and nutritional chemistry (lead, mercury, copper, zinc, arsenic levels). |
(Blood Cultures $\rightarrow$ Light Blue $\rightarrow$ Red $\rightarrow$ Gold $\rightarrow$ Light Green $\rightarrow$ Lavender $\rightarrow$ Gray).
Tube Inversion & Handling Rules
Mixing additives with blood must occur immediately after removing each tube from the holder:
- Never Shake: Vigorous shaking causes mechanical trauma to erythrocyte cell membranes, resulting in hemolysis (rupture of red blood cells). Hemolyzed specimens falsely spike potassium, LD, and magnesium levels and will be rejected by the laboratory.
- What One Inversion Means: A complete inversion consists of turning the wrist 180 degrees until the air bubble reaches the opposite end, and turning it back 180 degrees.
- Light Blue Special Inversion Count: Light blue sodium citrate tubes require only 3 to 4 inversions. Over-mixing can activate platelets and alter coagulation factor measurements.
The 9:1 Ratio & Winged Infusion (Butterfly) Trap
Two of the most frequently missed questions on the NHA CPT examination involve the light blue top tube:
- The Strict 9:1 Blood-to-Anticoagulant Ratio: Light blue tubes contain 0.109M (3.2%) buffered sodium citrate. They must be filled to within ±10% of the indicator fill line. An underfilled tube (short draw) has excess liquid citrate relative to blood plasma, which artificially prolongs the PT and aPTT clotting times, resulting in sample rejection (QNS — Quantity Not Sufficient).
- The Butterfly Discard Tube Rule: When using a winged infusion set (butterfly needle) with evacuated tubes, the 12-inch plastic tubing contains approximately 0.5 to 1.0 mL of air (dead space). If a light blue tube is drawn first, this air is pulled into the tube, causing an underfill. Therefore, when drawing a coagulation tube with a butterfly needle, you must draw a non-additive discard tube first (a plain red top or clear discard tube) to purge the air from the tubing before puncturing the light blue tube. The discard tube does not need to be filled completely.
Needle Gauges and Venipuncture Angles
| Gauge & Color Code | Length | Clinical Usage |
|---|---|---|
| 21 Gauge (Green) | 1.0 to 1.5 inches | Standard routine adult venipuncture needle. Optimal balance between flow rate and minimal hemolysis in antecubital veins. |
| 22 Gauge (Black) | 1.0 to 1.5 inches | Used for adults with smaller, fragile veins, or pediatric patients. |
| 23 Gauge (Light Blue) | 0.75 inches | Standard butterfly needle. Used on hand veins, geriatric veins, pediatric patients, and rolling or collapsed veins. |
| 16–18 Gauge (Pink / Yellow) | 1.5 inches | Large-bore needle reserved for blood donor collection and autologous blood units to prevent hemolysis under high vacuum. |
Insertion Angles and Tourniquet Times
- Standard Antecubital Venipuncture: Insert bevel up at an angle of 15 to 30 degrees.
- Hand Vein / Dorsal Venipuncture: Insert at a shallow angle of 10 to 15 degrees to avoid hitting fragile nerve endings or penetrating through the opposite vein wall.
- Tourniquet Limit: Never leave a tourniquet on the arm for longer than 1 minute (60 seconds). Leaving it on longer causes hemoconcentration (pooling of large proteins and cellular elements) and local stasis, falsely elevating potassium, albumin, enzymes, and calcium. Apply tourniquet 3 to 4 inches above the puncture site.
Order of Antecubital Vein Selection
The CLSI standard designates the order of choice for venipuncture in the antecubital fossa:
- Median Cubital Vein (1st Choice): Located in the center of the antecubital fossa. It is well-anchored, less painful, and farthest from major nerves and the brachial artery.
- Cephalic Vein (2nd Choice): Located on the lateral (outer / thumb) aspect. Ideal for obese patients where the median cubital is non-palpable, though prone to rolling.
- Basilic Vein (3rd Choice / Last Resort): Located on the medial (inner / pinky) aspect. It rolls easily and lies directly adjacent to the median cutaneous nerve and the brachial artery. Puncture here carries the highest risk of accidental arterial puncture and permanent nerve injury.
Frequently Asked Questions
Why is blood culture drawn first in the order of draw?
Blood cultures must be drawn first to maintain strict sterility. Any skin bacteria or cross-contamination from non-sterile tube stoppers would contaminate the culture bottles, leading to false-positive sepsis diagnoses.
What happens if a light blue tube is underfilled?
Underfilling a sodium citrate tube alters the mandatory 9:1 blood-to-anticoagulant ratio. The excess liquid anticoagulant dilutes the plasma, falsely prolonging clotting times (PT/INR and aPTT). The laboratory will reject the specimen as QNS.
How many times should blood collection tubes be inverted?
Most anticoagulant and clot-activator tubes require 8 to 10 gentle inversions (green, lavender, gray). Gold/tiger SST tubes require 5 inversions. Light blue sodium citrate tubes require only 3 to 4 gentle inversions. Plain glass red tubes require 0 inversions.
What is the maximum time a tourniquet can remain on?
A tourniquet must never remain in place for longer than 60 seconds (1 minute). Extended tourniquet application causes hemoconcentration and alters test results.
Sources
- Clinical and Laboratory Standards Institute (CLSI) Standard H3-A6 / GP41 — Procedures for the Collection of Diagnostic Blood Specimens by Venipuncture; Approved Standard (6th Edition).
- NHA Certified Phlebotomy Technician (CPT) Test Plan, National Healthcareer Association — Order of Draw, Additives, and Complications.
- OSHA Bloodborne Pathogens Standard (29 CFR 1910.1030) — Safety needles and biological specimen transport.
- QuizCram Phlebotomy Review Board — Verified October 24, 2026.